






How Does a Handheld Ultrasound Work? What's Inside a Wireless Probe
- 2026-11-03
- 51
- Guangzhou Sonostar Technologies Co., Limited
The question we hear most from clinic owners is not really technical. It is: "Something this small cannot possibly be as good as the machine in the hospital, can it?"
It is a fair question, and the honest answer requires understanding what changed and what did not. The physics of ultrasound never shrank. What shrank was everything around it.
1. The five things that used to fill a room
Think of a traditional ultrasound system as five separate jobs. Four of them no longer need to be in the machine.
| Component | Used to live in | Where it went |
|---|---|---|
| Transducer array (探头晶片阵列) | Inside the probe — always did, always will | Stayed in the probe. This is the one part that cannot move: it has to touch the patient. On a modern wireless probe it is 128–192 individual elements packed into a face a few centimetres wide. |
| Beamformer and processor (波束成形与图像处理) | A computing board the size of a desktop tower | Split. A small chip inside the probe handles the first stage; the heavy image reconstruction runs on the connected phone or tablet. |
| Display | A dedicated monitor on a cart | Your phone, tablet, or PC screen — hardware you already own. |
| Power supply | Mains power through a wall socket | A rechargeable lithium battery — typically 2,200 mAh or more, sometimes user-replaceable. |
| Data connection | A thick cable to the console | Wi-Fi — dual-band, transmitting images to the display device in real time. |
That is the whole trick. A conventional machine carried a computer, a monitor, and a power supply because in 1995 there was no other option. Today the clinician is already carrying a device with a screen, a processor, and a battery in their pocket. The probe only has to do the part that requires touching the patient.
2. What actually shrank — and what did not
This is where the honest part begins. Two things genuinely did not get smaller:
The physics of sound. Higher frequency gives finer detail but shallower penetration; lower frequency goes deeper but shows less detail. No amount of miniaturisation changes that trade-off. It is why a linear probe at 7.5–10 MHz is used for superficial structures and vascular access, while a convex probe at 3.2–5 MHz is used for the abdomen.
The value of physical aperture. A larger probe face with more elements generally captures more information. Handheld probes have improved dramatically here — 64 channels driving 192 elements is now common — but a premium cart system still has physical advantages for deep abdominal imaging.
What shrank is everything else: the computer, the screen, the power supply, the cable, and — importantly — the price of both the hardware and the room it used to need.

3. Why this matters for image quality
When you compare devices, four numbers on the specification sheet explain most of the difference you will actually see:
Number of elements — more elements means more independent sound sources, which improves resolution and detail. 128 is standard; 192 is better.
Number of channels — how many elements can be processed at once. 64 channels is a common configuration in wireless probes today.
Frequency range — determines whether the probe is built for depth or for surface detail. This is why one probe cannot do everything well.
Scanning depth — a convex probe on a modern handheld unit typically covers 90–305 mm, which is enough for most abdominal work.
Notice that none of these are "smallness" penalties. They are design choices. A well-built handheld probe with 192 elements and 64 channels will outperform an older cart machine with fewer elements — it is simply that the best cart systems still sit at the top of the range.
4. Where small still means compromise
Being straight about this is more useful than pretending otherwise:
Battery life. One to three hours of continuous scanning is typical. For a long outreach session, a user-replaceable battery design matters more than raw capacity, because a spare can be swapped in seconds.
Sustained scanning heat. A small sealed device doing continuous processing warms up. Devices intended for long sessions are designed with this in mind; very cheap units sometimes are not.
Deep imaging in larger patients. This remains the clearest gap versus a premium cart system, and it is a legitimate reason to keep a cart machine available.
Dependence on the display device. The probe relies on a phone or tablet. That is usually a strength, but it does mean the workflow depends on that device being charged, available, and running a compatible app.
5. One probe or three? The practical answer
Because probe type determines what you can see, the real configuration question is not size but array type:
Convex — lower frequency, wider and deeper view: abdomen, obstetrics, bladder.
Linear — higher frequency, superficial detail: vascular access, tendons, thyroid, small parts.
Phased array — small footprint for imaging between the ribs: cardiac.
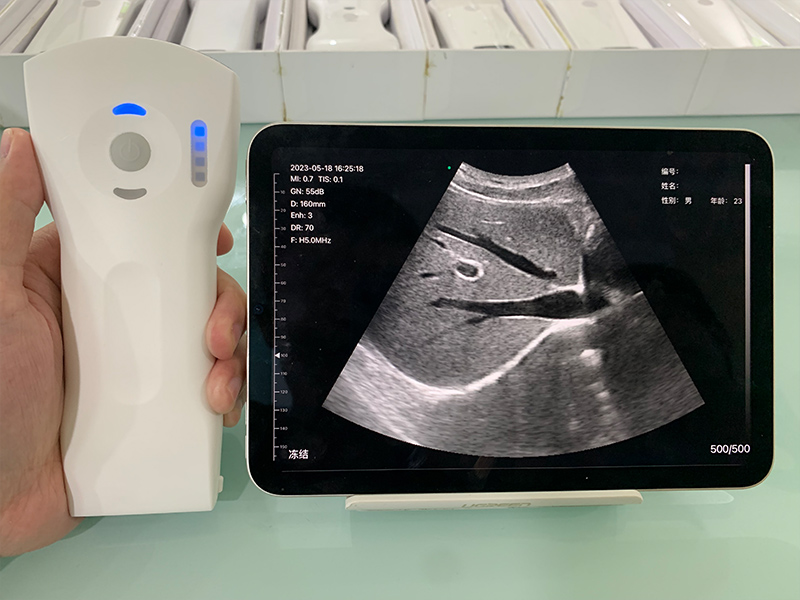
A clinic with a mixed caseload usually does best with a combined unit. Our three-in-one probe design puts convex, linear, and phased array in one device, which is what allows a single handheld unit to serve several departments rather than one. For volume imaging, dedicated probes still have an edge — which is why some facilities buy both.
6. Reading a spec sheet in five minutes
If you are comparing models, ask for these five things and ignore the marketing:
Elements and channels (192 / 64 is a solid modern configuration)
Frequency range and maximum scanning depth
Battery capacity and whether it is user-replaceable
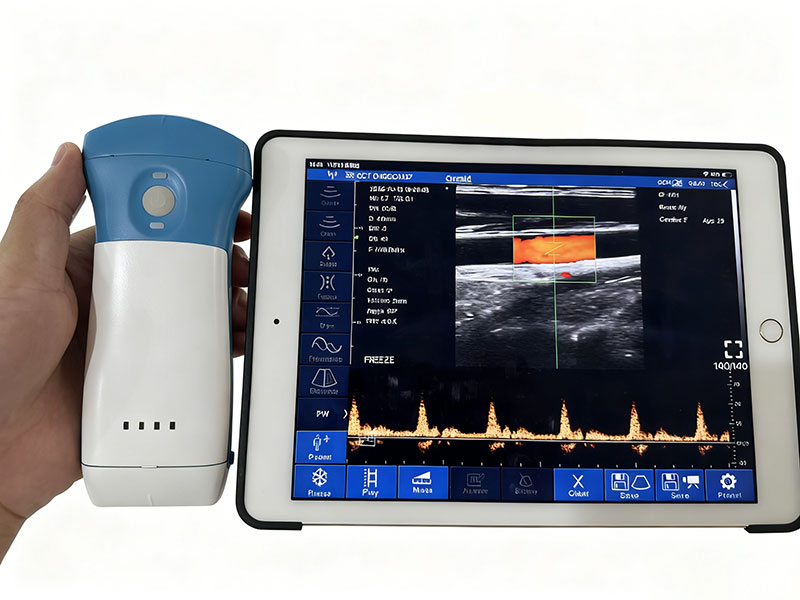
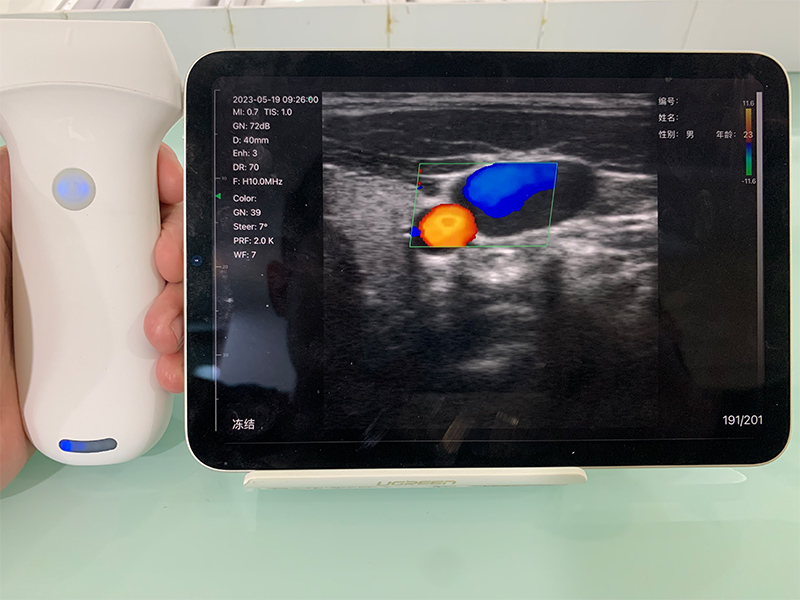
Which imaging modes are included — B, B/M, Colour, Power Doppler, Pulsed Wave — and whether any of them require an ongoing subscription
How images are exported (DICOM) and whether they can be attached to your existing record system
That last point is worth emphasising: on a handheld system, software is the machine. Two probes with identical hardware can behave very differently depending on the app, the presets, and whether key functions sit behind a paywall. Our overview of how Doppler detects blood flow covers one of the functions most often affected.
Frequently asked questions
Disclaimer: This article explains general ultrasound technology for information purposes and does not constitute clinical, diagnostic, or procurement advice. Device performance varies by model and configuration; always evaluate equipment against your own clinical requirements and local regulatory registration.




 Home
 Product
 News
 Contact
